What Patients Should Know About Dr. Eliran Mor And IVF
Fertility care is about more than medication. There are two-week waits and constant appointments, and you have to trust a Doctor with something deeply personal.
Doctor Eliran Mor
Dr. Eliran Mor
Dr. Eliran Mor
For more than twenty years, Dr. Eliran Mor, a Southern California reproductive endocrinologist, has treated fertility patients, including with in vitro fertilization (IVF).
Who Is Dr. Mor?
His training path crosses two continents. Dr. Mor earned his medical degree in 1997 at the Sackler School of Medicine at Tel Aviv University, then moved to Brooklyn for a four-year obstetrics and gynecology residency at New York Methodist Hospital. In 2001 he came to Los Angeles for a three-year fellowship in reproductive endocrinology and infertility at the University of Southern California, finishing in 2004.
He is board certified in two fields: reproductive endocrinology and infertility, and obstetrics and gynecology. People often overlook the second credential, yet it means he is also trained in surgery and obstetrics, which helps when a fertility problem has a structural cause, such as fibroids or an unusually shaped uterus.
His professional memberships include the American Society for Reproductive Medicine, the Pacific Coast Reproductive Society, the Society of Laparoendoscopic Surgeons, and the American College of Obstetricians and Gynecologists. Dr. Mor also remains a clinical instructor at USC, which means he teaches alongside his clinical work. His command of English, Hebrew, French, and Spanish is useful in a city as linguistically diverse as Los Angeles.
He has researched topics such as polycystic ovary syndrome (PCOS), male factor infertility, blocked or damaged fallopian tubes, IVF stimulation protocols, congenital uterine differences, and pregnancy at advanced reproductive age. People are starting families later than they used to, and patients in that group benefit from a Doctor who knows what the research actually says about age.
 Age and IVF: What the Research Says
IVF Explained In Plain English
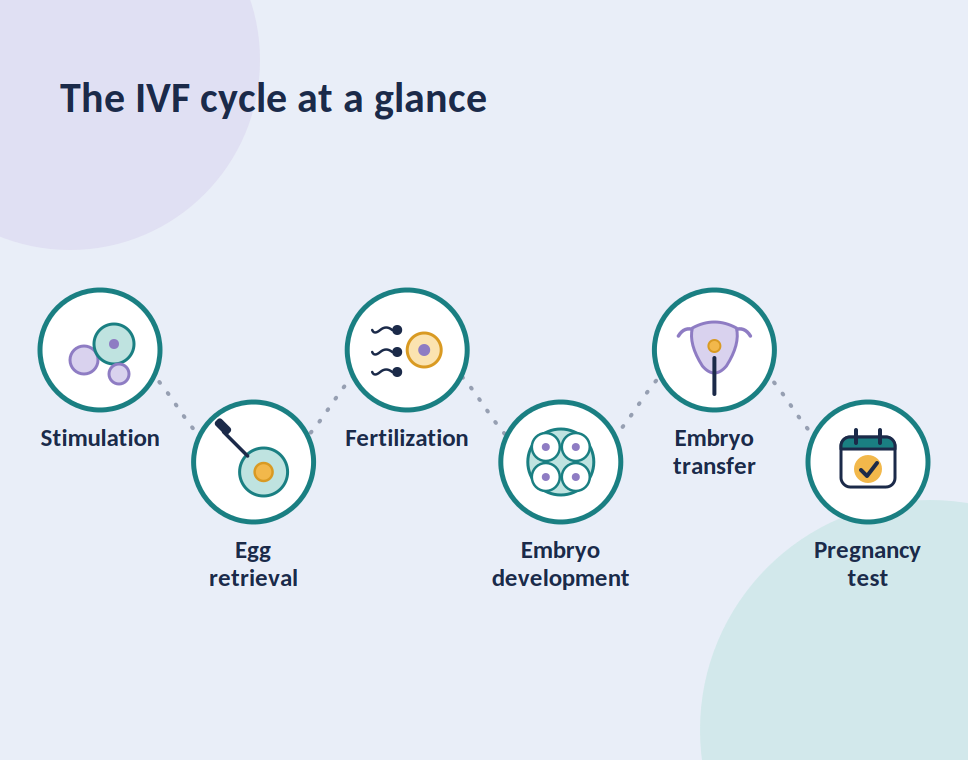
In a typical menstrual cycle, the body usually produces one mature egg. IVF tries to collect several, because more eggs means more chances at healthy embryos. So the first phase is about ovarian stimulation: a week or two of hormone injections, with frequent ultrasounds and blood tests to see how the follicles are developing. Doses often get adjusted along the way.
When the follicles are ready, a final “trigger” shot prepares the eggs for release. Roughly thirty-six hours after that, a short outpatient procedure under sedation retrieves the eggs. Most patients head home the same day.
After retrieval, the work moves to the laboratory. Eggs and sperm are combined, either by letting them meet in a dish or through intracytoplasmic sperm injection (ICSI), where an embryologist places a single sperm directly into an egg. Doctors often use ICSI when sperm count or movement is a concern. Over the following days the fertilized eggs develop into embryos.
Next comes the transfer. In some cycles a fresh embryo is transferred right away, and in others the embryos are frozen and one is transferred later in a frozen embryo transfer (FET). The procedure itself is fast, often over in minutes and usually without anesthesia. Then comes a wait of roughly two weeks before a pregnancy test. Many people describe that wait as the most stressful part of the whole process.
Details vary from patient to patient, including which medication protocol to use, how many embryos to transfer, whether to freeze first, and whether genetic testing makes sense. Those are the decisions where an experienced physician matters most.
One Doctor Throughout Treatment
Dr. Mor’s own description of his practice puts continuity front and center. According to him, he personally handles the major steps of a patient’s care, from consultations and after-hours questions to pelvic exams, ultrasounds, egg retrievals, embryo transfers, and any surgery that is needed.
At many fertility clinics, a rotating team means a patient may see a different physician at almost every visit. When you’re stressed and running on little sleep, explaining your history for the fourth time to someone new can feel exhausting. A single Doctor who already knows your history and your last cycle can spot patterns that a rotating cast of providers might miss.
Patient reviews on his Healthgrades profile point the same direction. Reviewers call him warm and honest and say he answers every question without rushing them. A few also praise his staff as helpful and easy to reach. Online reviews are personal stories rather than guarantees, and fertility outcomes depend on many factors that no Doctor controls.
Approach To New Techniques
Add-ons are popular in the fertility industry. New lab techniques and add-on procedures are marketed constantly, and a few of them have real evidence behind them. Many others do not. If you’re a patient, it’s hard to tell the difference, especially when you’re paying out of pocket and hoping for any edge.
Dr. Mor says he takes a conservative line. He adopts new interventions only after they have held up in multiple good studies. To stay current, he goes to monthly journal club sessions and educational seminars, and he attends at least two major reproductive medicine conferences every year.
A conservative approach doesn’t guarantee a better outcome, but it can make it less likely that a patient pays for something expensive that lacks solid evidence.
Genetic Testing And Other Reasons For IVF
Not everyone who uses IVF has trouble conceiving. Some patients choose it to lower the risk of passing on an inherited condition through preimplantation genetic testing, which is often still called PGD. A few cells are sampled from each embryo and analyzed before transfer, so embryos without a specific genetic variant can be chosen.
PGD is among Dr. Mor’s listed procedures, and one patient on his profile says they came to him for exactly that reason, since they carried a hereditary gene mutation and wanted to keep it from their children. In a different review, another patient says they froze eggs at age 34 and later used them in an IVF cycle with a partner.
Other procedures on his profile show how wide fertility care can be: assisted hatching, intrauterine insemination, ovulation induction, hysteroscopy, and robotic-assisted surgery. Not everyone needs IVF. Many people begin with simpler steps, and a good specialist should tell you honestly which path fits, even when that means a less intensive option.
Who Typically Needs IVF?
Blocked fallopian tubes are the classic example, because the egg and sperm cannot meet inside the body. Endometriosis, PCOS that doesn’t respond to milder treatment, and low ovarian reserve also lead many people to IVF. Male factor infertility is another common reason. Some people receive a diagnosis of unexplained infertility, where every test comes back normal and pregnancy still has not happened.
Age matters a great deal. Egg quantity and quality decline over time, and the decline picks up in the late thirties. Waiting isn’t always a mistake, but an early evaluation shows you what your options are.
Same-sex couples and single parents by choice also rely on IVF, often with donor eggs, donor sperm, or a gestational carrier.
Cost, Insurance, And Choosing A Clinic
In the United States, one IVF cycle often costs well into five figures once medications and monitoring are included, and many patients need more than one cycle. Insurance coverage varies a great deal by state, employer, and plan. California has been expanding its fertility coverage requirements, but what applies to you depends on your type of plan, so ask your insurer specific questions before you begin.
Several major carriers appear on Dr. Mor’s public profile, including Aetna, Anthem Blue Cross, Blue Cross Blue Shield, Cigna, and UnitedHealthcare. Networks shift, and fertility benefits are frequently managed separately from regular medical coverage, so use any online list as a starting point and confirm with both the office and your insurer.
Before choosing any specialist, consider asking these questions:
- Is the physician board certified in reproductive endocrinology and infertility?
- Will I see the same Doctor throughout, or a rotating team?
- How does the clinic decide which add-ons to recommend?
- Will the costs be laid out clearly before I commit?
- Who do I call with an urgent question at 10 p.m.?
It also makes sense to check a Doctor’s background. Dr. Mor’s Healthgrades listing shows no malpractice claims, sanctions, or board actions.
The Emotional Toll Of IVF
IVF is physically demanding, and the emotional load can be just as heavy. Injections, appointments, bills, and uncertainty pile up, and together they can strain even solid relationships. Many people need more than one attempt, which is normal but doesn’t make it easy.
Reviews of Dr. Mor often come back to how he and his staff treated patients. One couple describes a three-year journey with him that led to a second pregnancy. Another patient describes “graduating” from his office at eleven weeks of pregnancy, already expecting to miss the staff.
Choosing A Specialist
Millions of people have become parents with the help of IVF. It is also expensive and emotionally demanding, and the process is complicated enough that the choice of Doctor carries a lot of weight.
Dr. Mor is board certified in two specialties, trained at USC, still teaches there, and describes a practice built on personal involvement and evidence-based choices. If you’re considering IVF in the Los Angeles area, the questions listed above are a useful starting point for a consultation.
This article is for general informational purposes only and is not medical advice. Because every situation is different, please speak with a qualified healthcare provider about your own circumstances.